


Given who I am and what I do, I regularly get asked ‘my take on’ or ‘what the deal is with’ something. This is flattering and appreciated (it’s a source of inbound to stay on top of things and frankly gives me many topics for this newsletter). Something I have regularly noticed in the process of hearing questions, and in the discourse around many "‘story of the days” is the lack of first principles thinking and understanding.
Much if of the surprise and misunderstanding in the world of biomarkers, testing and technology can easily be anticipated and better understood with first principles thinking. This is important given we are increasingly using algorithms and technology to give us estimates of measures that can be of concern. If we understand the principles of the technology or measures, then their limitations become apparent as do sources of potential error - limiting our over interpretation and potential concerns.
Does Creatine Cause Kidney Issues?
Whilst this has been largely dismissed as false, it seems to be a myth which is hard to kill (Brandolini’s law strikes again). But where did the myth start from?
It started from system 1 thinking. It started from a lack of first principles understanding. Let me explain.
I will do my best to keep this simple enough - if doctors are overlooking this, I wouldn’t expect readers to be interested in all the minutiae so I will keep it high level. When a doctor tests kidney function, they are looking to understand glomerular filtration rate (GFR). This is quite difficult to do and as such estimates are used, to achieve a so-called eGFR (estimated GFR). In short this involves using certain substances that freely pass into the urine through the glomerulus (part of the kidney - the bit that does much of the filtering). If these substances increase in the blood, this suggests a reduction in GFR and thus worsening kidney function (because less of them are leaving the body in the urine and thus the kidney’s filtration function isn’t working properly). Two of these substances are Cystatin C, a protein produced throughout the body, and Creatinine which is a product of breakdown of muscle and digestion of protein.
Enter healthy, young, gym going males looking to impress others with their biceps and an apparent epidemic of reduced renal function. Except their kidneys were working. If we use system 2 thinking and understand the testing, we swiftly realise that the reduced eGFR is more likely the result of an increased muscle mass and/or creatine use, both of which will increase creatinine - neither of which impair kidney function (if anything, the opposite). If we use Cystatin C based measures or estimates in these individuals, we see normal kidney function measures.
In fact, there is research suggesting Cystatin C is also a better indicator of your kidney function in those with kidney disease. Why, you may ask - individuals with kidney disease have reduced muscle mass, so using creatinine based eGFR measures overestimates GFR.
This is not to say we shouldn’t use creatinine, or eGFR, it is to suggest we need to understand what is actually measured, what is estimated and sources of error.
As an aside….

How Much Sugar is in my Vitamin C Supplement!?
This is a very reasonable question, particularly given some of the flavoured supplements on the market. The answer may well be, some, which is probably too much (there’s no need for this - sugarphobic or not, there’s no need to add it to vitamin c, you could just use a tablet and not taste it) but how we know there is sugar in our viatmin c is where the story lies.
In a previous job I worked for a continuous glucose monitoring company which specifically targeted athletes. The sports supplement market can be quite messy at times, and there’s no shortage of added sugars. However, that isn’t always the case. I often had athletes mention to me they started avoiding certain foods or supplements that had hidden sugar in them or similar, which again is very reasonable (I too was shocked by how high my glucose got eating BBQ meat in Atlanta - turns out there was no shortage of sugar in the sauce).
So far so good, the continuous glucose monitors (CGMs) are alerting people to hidden sugars and people are making informed choices. Or are they misinformed?
CGMs, at least in their current incarnation, give an indication of concentration of glucose in the interstitial fluid (the fluid around your cells). BUT, they DON’T measure glucose. They estimate glucose, based on the signal from a reaction with an enzyme on their sampling filament, specifically, glucose oxidase. Those with basic knowledge of chemistry will agree this sounds perfect, but those who use these CGMs will quickly give you a lesson in the fact glucose oxidase reacts with more than just glucose! You guessed it, it does indeed interact with ascorbic acid (more commonly known as vitamin c), as well as the more commonly known interaction with aspirin.
So yes, your vitamin c supplement may well have sugar in it, but you’re better off learning that from the ingredients and nutritional information than relying on your CGM for it.
What’s My Body Fat Percentage?
The gold standard(s) measurement of body composition are DEXA scan or underwater weighing (the latter of which is cumbersome and a little old school so rarely used these days). The availability and cost of DEXA scans becoming more user friendly makes them an increasingly attractive measure of body composition (with the added benefit of bone mineral density measures also - more on bone health here).
Having said all this, DEXA scans are still too expensive for daily (or even probably monthly) use and come with a dose of radiation (albeit relatively small, depending on technique and machine, but often quoted as ~4 bananas).
Why is Radiation Measured in Bananas!?
The standard measure of radiation is a sievert (and portions thereof). To make this more tangible to people, in what has to be some of the best work done in this realm, these doses of radiation have been compared to the dose of radiation from eating a banana, known as ‘banana equivalent dose’. See below chart for a rough idea of banana equivalent dosages for various activities.
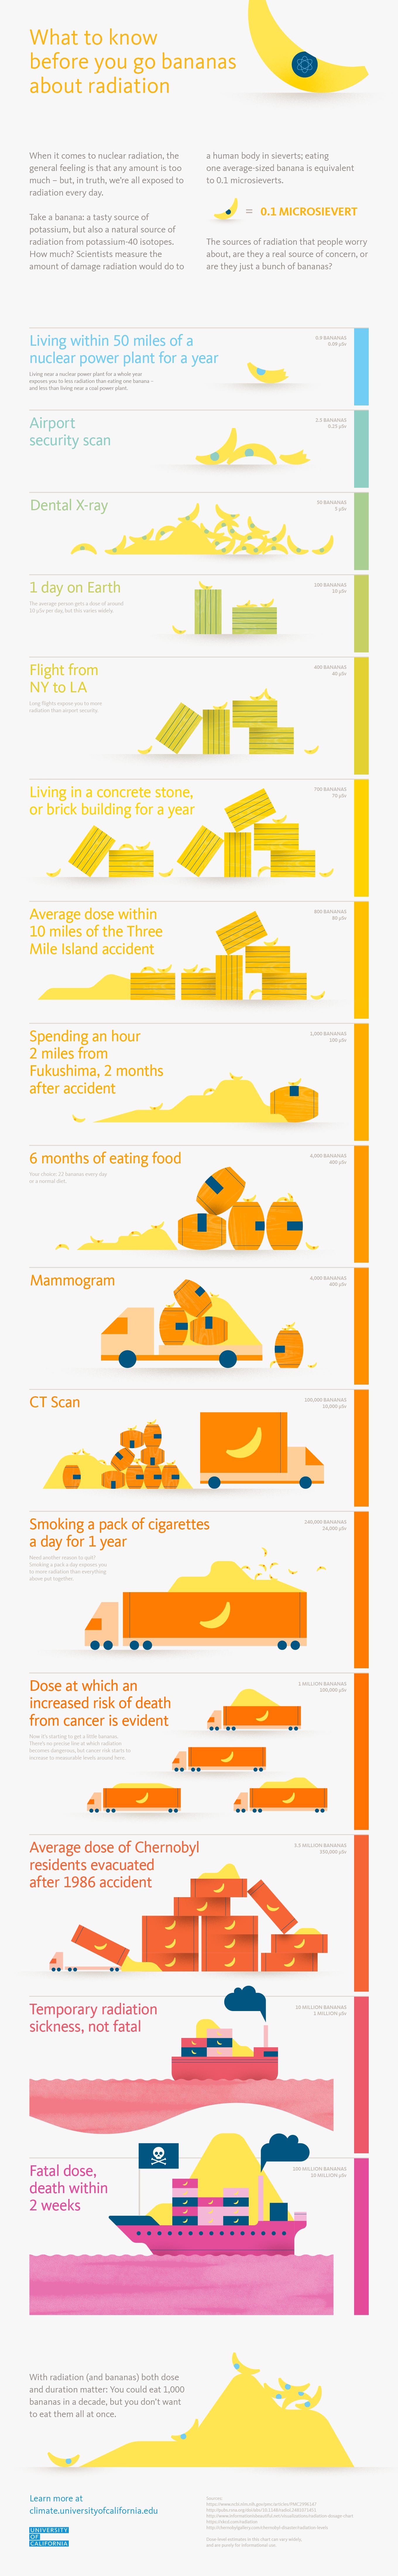
It is important to remember, that some of these doses are non-negotiable, and even small doses of unnecessary radiation should be avoided (remember total load matters) - thus it’s pertinent to avoid even 4 bananas of radiation dose if possible.
So using DEXA scans frequently isn’t an option, and bodyweight itself is thankfully (mostly) understood as a VERY crude measure of body composition. As such, folks are (rightly) looking for a tool to measure body composition more regularly (remember feedback is key to learning and success).
Enter bioelectrical impedance analysis (BIA). In short, this involves sending a very mild electrical current through your body to asses body composition. The resistance to this current gives an indication of fat, muscle, bone etc because they all have different electrical resistances. This should already be raising some questions, given nuances that need to be teased out with minimal input. In short, this impedance estimates your body composition measures from a large body of normative data, which is probably pretty close provided you look like the sample population. Now I can’t speak to any of those populations, but I am hoping it’s not like the rest of the tech world, where its’s largely a very homogenous middle aged white male sample that is used to build the model. In which case, higher muscle mass, or outlier anthropometry will yield inaccuracies, not to mention ethnic (and maybe biological sex) differences. On a shorter term timeframe, BIA systems are greatly impacted by hydration status (to be honest much of our testing is, it’s worth strandardising hydration status as best as possible for blood tests, DEXAs etc etc).
There is more here though, remember this isn’t a piece about trashing biometrics, it is a piece about needing to understand their limitations in certain cases. These BIA devices take many forms, often with a scale rolled into them. Some have handles, some don’t. Thinking this through and understanding the first principles of electric current, one should intuit that not having handles significantly changes the sources of potential error, the current is effectively going leg to leg in that case - thus any differences in body composition out of proportion above the legs from the sample population are not captured.
So whilst BIA systems can provide a convenient and accessible option for regularly keeping track of body composition, their output should be taken with a grain of salt. Much like there is now slightly more understanding that body mass (as measured on a scale) fluctuates regardless of meaningful body composition changes, similar (but probably to a lesser degree) could be said for BIA methodologies. Large changes in body composition are mostly not going to happen overnight and as such changes in body fat, muscle mass or bone mineral density are probably going to be imperceptible day to day so things like weekly averages should be used rather than any one day’s measures.
Challenges of Biomarker Development
Building technology and developing new biomarkers is exceedingly difficult. This is part of why I try not to be overly disparaging about these developments, we want the effort and the individuals doing it and likewise each step is one on the path to success.
One aspect that makes new biomarkers, wearables or similar difficult to develop at times is the absence of a gold standard. I was discussing with someone continuous blood pressure measures (there is already a continuous BP wearable on the market in Europe link here if you’re interested) and the difficulty they pose. The issue is not taking blood pressure, in fact, that’s relatively straight forward. The problem is doing so during less metabolically stable conditions such as during exercise, when blood pressure can been extremely high (~5x normal). We have the potential for a gold standard measure here, but it’s very difficult to do and it’s foreseeable that this isn’t always possible for all metrics for example biological aging clocks (for those unfamiliar I touched on them here).
This then raises another challenge, which is understanding newly continuous but previously discrete measures. Blood pressure as the example here; we have no idea what ‘normal’ or ‘ideal’ blood pressure is, or isn’t in many day to day situations (and to be honest blood pressure has some of the best insights in this regard). This is something I dissected when it comes to lactate and continuous lactate monitors.
Other Common Misunderstandings in Wearables:
Heart rate and PPG sensors accuracy, which I wrote about that here.
Using HRV as a continuous stress monitor as Marco Altini wrote about here.
Over interpreting sleep staging in sleep wearables - stick to two phase measures (sleep/wake) as measures of quality, accuracy of sleep stage prediction isn’t yet great.
Using and trusting composite scores rather than the components thereof to make sense of them.
Hopefully this article has served as a stimulus to think twice when looking at any result (wearable, blood test etc). I want to reiterate this is about us using tools better (or deciding not to if you so wish) because we better understand them and their limitations. They often aren’t perfect, nor do they necessarily need to be for them to show some utility. Having said that, knowing when they are off the mark, and potentially why, is crucial if we are going to use them - don’t outsource your thinking.
References:
Antonio J, Candow DG, Forbes SC, Gualano B, Jagim AR, Kreider RB, Rawson ES, Smith-Ryan AE, VanDusseldorp TA, Willoughby DS, Ziegenfuss TN. Common questions and misconceptions about creatine supplementation: what does the scientific evidence really show? J Int Soc Sports Nutr. 2021 Feb 8;18(1):13. doi: 10.1186/s12970-021-00412-w. PMID: 33557850; PMCID: PMC7871530.
Pottel H, Delanaye P, Cavalier E. Exploring Renal Function Assessment: Creatinine, Cystatin C, and Estimated Glomerular Filtration Rate Focused on the European Kidney Function Consortium Equation. Ann Lab Med. 2024 Mar 1;44(2):135-143. doi: 10.3343/alm.2023.0237. Epub 2023 Nov 1. PMID: 37909162; PMCID: PMC10628758.
Nedeljkovic D, Baltic S, Todorovic N, Ostojic SM. Creatine Intake Is Not Associated With Elevated Circulating Cystatin C Levels in Individuals With and Without Kidney Dysfunction in the General Population. J Am Nutr Assoc. 2025 Jan 8:1-4. doi: 10.1080/27697061.2024.2432484. Epub ahead of print. PMID: 39778146.
Shlipak MG, Matsushita K, Ärnlöv J, Inker LA, Katz R, Polkinghorne KR, Rothenbacher D, Sarnak MJ, Astor BC, Coresh J, Levey AS, Gansevoort RT; CKD Prognosis Consortium. Cystatin C versus creatinine in determining risk based on kidney function. N Engl J Med. 2013 Sep 5;369(10):932-43. doi: 10.1056/NEJMoa1214234. PMID: 24004120; PMCID: PMC3993094.
Bowler AM, Whitfield J, Marshall L, Coffey VG, Burke LM, Cox GR. The Use of Continuous Glucose Monitors in Sport: Possible Applications and Considerations. Int J Sport Nutr Exerc Metab. 2022 Dec 26;33(2):121-132. doi: 10.1123/ijsnem.2022-0139. PMID: 36572039.
MacDougall JD, Tuxen D, Sale DG, Moroz JR, Sutton JR. Arterial blood pressure response to heavy resistance exercise. J Appl Physiol (1985). 1985 Mar;58(3):785-90. doi: 10.1152/jappl.1985.58.3.785. PMID: 3980383.
How do we tell folks to use their brains without saying, “please use your brain!!” Great explanations, as always!!!